Hello, I’m Gil Wolfe, professor, neurologist, and clinical researcher specializing in autoimmune neuromuscular disorders, particularly generalized myasthenia gravis, or gMG. From an investigational standpoint, I have worked on clinical trials and outcome measure development in the MG space for 3 decades.
From a clinical standpoint, throughout my career, I’ve cared for many patients living with this complex and often unpredictable disease. It has been uplifting and energizing to witness the advances we have made in pharmacotherapeutics, particularly in the last decade, in MG. It has not only expanded our therapeutic options but has had real-world benefits for our patients.
Today, I’ll be speaking on behalf of Amgen, who has compensated me for my participation.
I’ll be walking you through the pivotal phase 3 MINT study that evaluated UPLIZNA® (inebilizumab-cdon), a humanized anti‑CD19 monoclonal antibody designed to target a broad range of pathogenic autoantibody-producing B-cell populations, including plasmablasts and plasma cells.
Let’s review the indication and important safety information of UPLIZNA.
INDICATIONS
UPLIZNA® (inebilizumab-cdon) is indicated in adult patients for the treatment of: anti-aquaporin-4 (AQP4) antibody positive neuromyelitis optica spectrum disorder (NMOSD); Immunoglobulin G4-related disease (IgG4-RD); anti-acetylcholine receptor (AChR) or anti-muscle specific tyrosine kinase (MuSK) antibody positive (Ab+) generalized myasthenia gravis (gMG).
IMPORTANT SAFETY INFORMATION CONTRAINDICATIONS
UPLIZNA® (inebilizumab-cdon) is contraindicated in patients with a history of a life-threatening infusion reaction to UPLIZNA, active hepatitis B infection, or active or untreated latent tuberculosis.
Please see full Prescribing Information at UPLIZNAhcp.com and additional Important Safety Information later in this video.
The MINT primary endpoint was the Myasthenia Gravis Activities of Daily Living Scale (or MG-ADL). This scale is a patient-reported assessment that reflects how gMG affects daily function and has served as the primary outcome measure in all gMG trials for targeted therapies leading to FDA approvals to date.
Before we discuss the study, let’s take a moment to understand how this disease impacts patients.
Generalized myasthenia gravis is a chronic autoimmune disease marked by fatigable muscle weakness that can significantly interfere with daily activities and independence.
Despite advances in standard of care, many patients continue to experience persistent symptom fluctuation. Many patients remain undertreated, with persistent and fluctuating symptoms that impair daily functioning. Despite the rapidly evolving treatment landscape, challenges remain in the management of gMG, which can lead to substantial disease burden for patients.
CD19+ plasmablasts and plasma cells generate the pathogenic autoantibodies that impair neuromuscular transmission. Plasmablasts are believed to be the primary producers of anti‑MuSK antibodies, whereas longer‑lived plasma cells predominantly produce anti‑AChR antibodies.
These autoantibodies bind to and damage essential postsynaptic proteins at the neuromuscular junction, disrupting communication between nerve and muscle, and driving the symptoms patients experience.
UPLIZNA is the first and only FDA‑approved therapy for gMG that targets CD19‑expressing B cells.
CD19 expression starts from early B-cell development and persists through maturation—importantly, this means CD19 is present on antibody-producing plasmablasts and plasma cells and serves as a point for upstream intervention at a key source of anti-AChR- and anti-MuSK-antibody production.
Although the exact mechanism by which UPLIZNA exerts its effect is unknown, UPLIZNA selectively targets CD19+ plasmablasts and plasma cells. Once bound, UPLIZNA effectively depletes these cells through antibody‑dependent cellular cytotoxicity, or ADCC, reducing populations that drive autoantibody production and immune-mediated damage.
By targeting these upstream antibody‑producing cells, UPLIZNA addresses a key source of disease activity.
With this rationale in mind, we can look more closely at the MINT study. Among phase 3 randomized, placebo‑controlled biologic trials in gMG to date, MINT is notable as:
- The largest study to include both anti‑AChR and anti‑MuSK antibody‑positive participants
- The study with the most anti‑MuSK‑positive participants enrolled, and
- The longest randomized controlled period for the anti‑AChR subpopulation
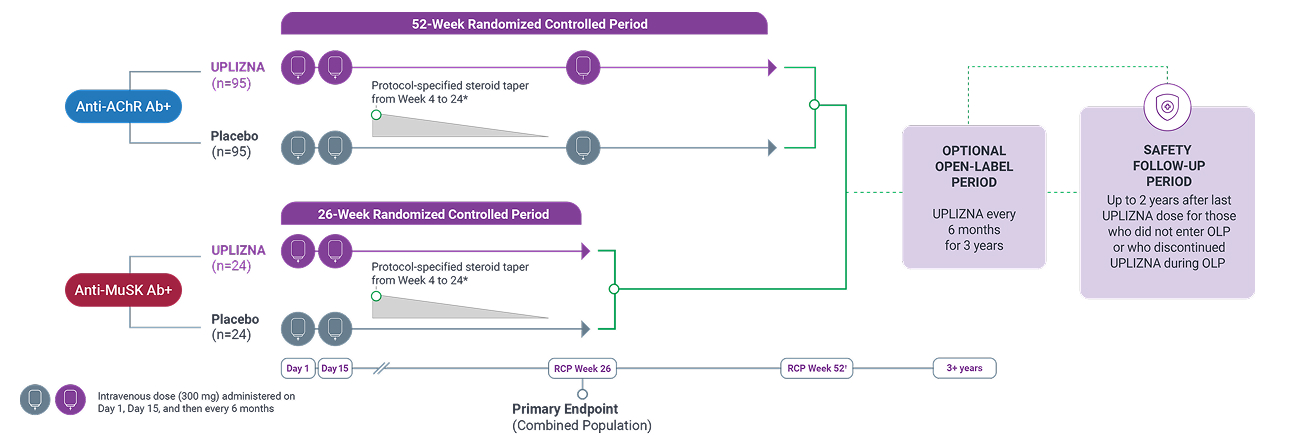
The MINT study was a randomized double blind, placebo-controlled trial, in which the primary endpoint was MG-ADL score at 26 weeks in the combined anti-AChR- and anti-MuSK antibody-positive populations.
There were 2 randomized control periods: 52 weeks for the anti-AChR-Ab+ participants and 26 weeks for anti-MuSK-Ab+ participants.
Week 26 was selected as the primary endpoint for both cohorts to align with other gMG trials, but the RCP for the anti-AChR-Ab+ participants was extended through 52 weeks to allow for further collection of long-term data, with a placebo comparison.
Participants received either UPLIZNA or placebo. UPLIZNA is administered as an intravenous infusion twice yearly after two initial loading doses.
At the end of the RCPs, all participants were offered an optional 3-year open label period and a mandated safety follow-up period for up to 2 years after the last UPLIZNA dose.
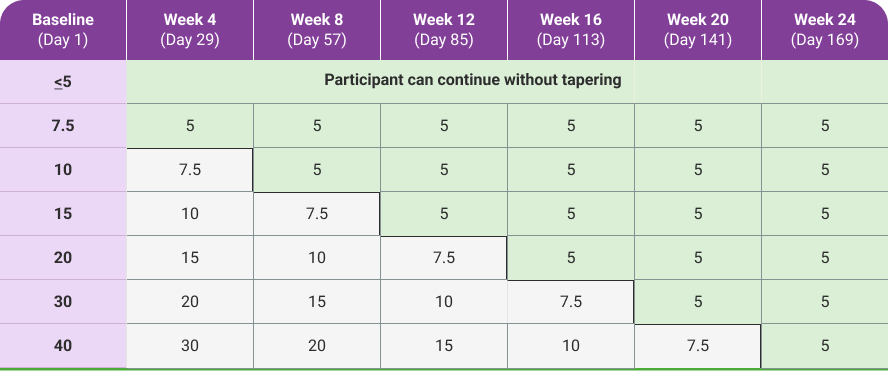
And the MINT study was one of the rare studies to incorporate a prespecified steroid‑tapering schedule—a key design feature. This assessed the utility of UPLIZNA within the broadly accepted clinical practice of minimizing long-term steroid exposure during treatment of gMG.
All participants receiving steroids at baseline underwent a scheduled taper from week 4 to 24 during the randomized control period, to a final target of 5 milligrams per day or less.
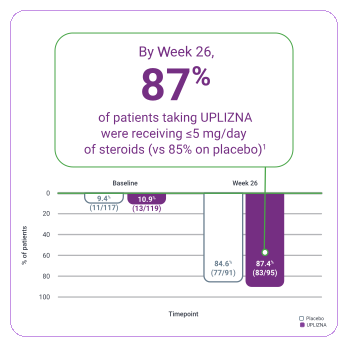
In the combined UPLIZNA and placebo populations, 82% of participants were receiving over 5 milligrams per day of prednisone or equivalent at baseline with an average dose of 17.5 milligrams per day at baseline. The percentage of participants reaching this target dose was similar across both the UPLIZNA and placebo arms of the trial. By Week 26, 87% of participants taking UPLIZNA were receiving 5 milligrams per day or less of steroids compared to 85% on placebo.
Finally, before reviewing efficacy outcomes, it’s important to understand who was enrolled in the MINT study.
The participants in the MINT study closely reflected patients with gMG in clinical practice in terms of age, disease duration, and baseline severity.
In the MINT study, 95% of patients were classified as mild to moderate. Overall, the trial evaluated UPLIZNA in a clinically meaningful population.
By enrolling substantial anti-AChR and MuSK-antibody positive cohorts, MINT also became the largest phase 3 study to include both key serotypes to date, as mentioned previously.
Now, before we discuss the efficacy outcomes, I’d like to offer a quick refresher on the scales used in this study. MG-ADL, which stands for Myasthenia Gravis Activities of Daily Living, is a patient‑reported, 8‑item scale that ranges from 0 to 24. It measures the impact of gMG symptoms on everyday functions such as speech, chewing, breathing, and limb function, with higher scores indicating greater disability.
QMG, which stands for Quantitative Myasthenia Gravis score, is a clinician‑administered, 13‑item assessment with scores that range from 0 to 39. It quantifies muscle weakness and fatigability across key muscle groups in gMG, with higher scores reflecting more severe disease.
The primary endpoint, change from baseline in MG-ADL at Week 26 in the combined anti-AChR-Ab+ and anti-MuSK-Ab+ population, demonstrated a 4.2-point improvement from baseline with UPLIZNA compared to 2.2-points with placebo, reflecting meaningful clinical benefit.
Now, let’s review the safety profile observed in MINT. This table lays out the safety findings from the trial, including all adverse events occurring in at least 5% of participants and a greater incidence in the UPLIZNA arm vs the placebo arm. In the RCP, the most common adverse events were headache, infusion-related reaction, nasopharyngitis, cough, and urinary tract infection.
Let’s take a quick look at the key secondary outcomes from Week 26.
- First, in the combined population, UPLIZNA produced a 4.8‑point improvement in QMG, compared to 2.3 with placebo
- Next, looking at the anti‑AChR-Ab+ group, UPLIZNA achieved a 4.2‑point improvement in MG‑ADL versus 2.4 with placebo
- For QMG in this same subgroup, UPLIZNA improved scores by 4.4 points, compared with 2 points for placebo
- And finally, in the anti‑MuSK-Ab+ group, UPLIZNA delivered a 3.9‑point improvement in MG‑ADL versus 1.7 with placebo
- For QMG in the anti-MuSK‑Ab+ cohort, UPLIZNA improved scores by 5.2 points, compared to 3 points with placebo, but was not statistically significant
Please note that the secondary endpoints in the MINT study were evaluated using a rigorous prespecified statistical hierarchy.
Let’s look more closely at the 52-week randomized controlled data—the longest evaluated for the anti-AChR-Ab+ subpopulation in any gMG trial for an FDA-approved biologic, to date.
Those receiving UPLIZNA achieved a 4.7-point reduction in MG-ADL from baseline at one year, compared to 1.9 points with placebo, demonstrating durable, sustained improvement over one year.
A meaningful proportion of patients responded to treatment, with 72.3% of those receiving UPLIZNA achieving at least a 3-point improvement in MG‑ADL, compared with 45.2% on placebo.
Overall, these secondary and exploratory endpoint results reinforce the deep durable effect of UPLIZNA, with consistent improvements seen in both MG-ADL and QMG across subpopulations, as steroids were tapered to 5 mg or less a day.
Before I summarize what we’ve discussed today, let’s take a moment to review the indication and important safety information of UPLIZNA.
INDICATIONS
UPLIZNA® (inebilizumab-cdon) is indicated in adult patients for the treatment of: anti-aquaporin-4 (AQP4) antibody positive neuromyelitis optica spectrum disorder (NMOSD); Immunoglobulin G4-related disease (IgG4-RD); anti-acetylcholine receptor (AChR) or anti-muscle specific tyrosine kinase (MuSK) antibody positive (Ab+) generalized myasthenia gravis (gMG).
IMPORTANT SAFETY INFORMATION AND INDICATIONS
CONTRAINDICATIONS
UPLIZNA® (inebilizumab-cdon) is contraindicated in patients with a history of a life-threatening infusion reaction to UPLIZNA, active hepatitis B infection, or active or untreated latent tuberculosis.
WARNINGS AND PRECAUTIONS
- Infusion Reactions: Infusion reactions, including anaphylaxis, can occur. Symptoms can include headache, nausea, somnolence, dyspnea, fever, myalgia, rash, or palpitations. Infusion reactions were observed in 9.3%, 7.4%, and 10.1% of patients treated with UPLIZNA during the randomized controlled periods (RCPs) of Study 1 in patients with NMOSD, Study 2 in patients with IgG4-RD, and Study 3 in patients with gMG, respectively. Infusion reactions were most common with the first infusion but were also observed during subsequent infusions.
- Administer pre-medication with a corticosteroid, an antihistamine, and an antipyretic. For life-threatening infusion reactions, immediately and permanently stop UPLIZNA and administer appropriate supportive treatment. For less severe infusion reactions, management may involve temporarily stopping the infusion, reducing the infusion rate, and/or administering symptomatic treatment.
- Infections: Serious, including life-threatening or fatal, bacterial, fungal, and new or reactivated viral infections have been observed during and following completion of treatment with B-cell depleting therapies, including UPLIZNA. The most common infections reported by UPLIZNA-treated patients in the NMOSD randomized and open-label clinical trial periods for NMOSD were urinary tract infection (20%), nasopharyngitis (13%), upper respiratory tract infection (8%), and influenza (7%). In the IgG4-RD RCP, the most common infections reported by UPLIZNA-treated patients were urinary tract infection, influenza, and pneumonia. In the gMG RCP, the most common infections reported by UPLIZNA-treated patients were urinary tract infection and nasopharyngitis. Delay UPLIZNA administration in patients with an active infection until the infection is resolved.
Possible Increased Risk of Immunosuppressant Effects with Other Immunosuppressants: If combining UPLIZNA with another immunosuppressive therapy, consider the potential for increased immunosuppressive effects.
Hepatitis B Virus (HBV) Reactivation: HBV reactivation has been observed with B-cell-depleting therapies, including UPLIZNA. Fulminant hepatitis, hepatic failure, and death caused by HBV reactivation have occurred in patients treated with B-cell depleting therapies. HBV reactivation was observed in a patient treated with UPLIZNA during the gMG clinical trial and in the postmarketing setting. Patients with active or chronic HBV infection were excluded from clinical trials. Perform HBV screening in all patients before initiation of treatment. Do not administer to patients with active HBV confirmed by positive results for HBsAg and anti-HB tests. For patients who are negative for HBsAg and positive for HBcAb, or who are carriers of HBV (i.e., HBsAg+), consult liver disease experts before starting and during treatment.
Progressive Multifocal Leukoencephalopathy (PML): Although no confirmed cases of PML were identified in UPLIZNA clinical trials, JC virus infection resulting in PML has been observed in patients treated with other B-cell-depleting antibodies and other therapies that affect immune competence. In UPLIZNA clinical trials one subject died following the development of new brain lesions for which a definitive diagnosis could not be established, though the differential diagnosis included an atypical NMOSD relapse, PML, or acute disseminated encephalomyelitis. At the first sign or symptom suggestive of PML, withhold UPLIZNA and perform an appropriate diagnostic evaluation. MRI findings may be apparent before clinical signs or symptoms. Typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes.
Tuberculosis
Patients should be evaluated for tuberculosis risk factors and tested for latent infection prior to initiating UPLIZNA. Consider anti-tuberculosis therapy prior to initiation of UPLIZNA in patients with a history of latent active tuberculosis in whom an adequate course of treatment cannot be confirmed, and for patients with a negative test for latent tuberculosis but having risk factors for tuberculosis infection. Consult infectious disease experts regarding whether initiating anti-tuberculosis therapy is appropriate before starting treatment.
Vaccinations
Administer all immunizations according to immunization guidelines at least 4 weeks prior to initiation of UPLIZNA. The safety of immunization with live or live-attenuated vaccines following UPLIZNA therapy has not been studied, and vaccination with live-attenuated or live vaccines is not recommended during treatment and until B-cell repletion.
Vaccination of Infants Born to Mothers Treated with UPLIZNA During Pregnancy
In infants of mothers exposed to UPLIZNA during pregnancy, do not administer live or live-attenuated vaccines before confirming recovery of B-cell counts in the infant. Depletion of B-cells in these exposed infants may increase the risks from live or live-attenuated vaccines. Non-live vaccines, as indicated, may be administered prior to recovery from B-cell and immunoglobulin level depletion, but consultation with a qualified specialist should be considered to assess whether a protective immune response was mounted.
- Reductions in Immunoglobulins: There may be a progressive and prolonged hypogammaglobulinemia or decline in the levels of total and individual immunoglobulins such as immunoglobulins G and M (IgG and IgM) with continued UPLIZNA treatment. Monitor the levels of quantitative serum immunoglobulins during treatment with UPLIZNA, especially in patients with opportunistic or recurrent infections, and until B-cell repletion after discontinuation of therapy. Consider discontinuing UPLIZNA therapy if a patient with low immunoglobulin G or M develops a serious opportunistic infection or recurrent infections, or if prolonged hypogammaglobulinemia requires treatment with intravenous immunoglobulins.
- Fetal Risk: Based on animal data, UPLIZNA can cause fetal harm due to B-cell lymphopenia and reduce antibody response in offspring exposed to UPLIZNA even after B-cell repletion. Transient peripheral B-cell depletion and lymphocytopenia have been reported in infants born to mothers exposed to other B-cell-depleting antibodies during pregnancy. Advise females of reproductive potential to use effective contraception while receiving UPLIZNA and for at least 6 months after the last dose.
ADVERSE REACTIONS
- The most common adverse reactions (at least 10% of patients treated with UPLIZNA and greater than placebo): urinary tract infection and arthralgia in NMOSD; urinary tract infections and lymphopenia in IgG4-RD; headache and infusion-related reaction in gMG.
Please see UPLIZNA full Prescribing Information available on this site.
Welcome back!
In summary, the MINT study reinforces the value of UPLIZNA in anti-AChR- or anti-MuSK-Ab+ gMG:
- UPLIZNA has a novel, upstream CD19‑targeted mechanism, depleting the plasmablasts and plasma cells that drive antibody production
- Participants in MINT saw a clinically meaningful and statistically significant improvement in MG-ADL vs placebo at the end of the combined RCP at Week 26 as steroids were tapered to ≤5mg/day. Improvement in MG-ADL vs placebo was sustained in anti-AChR-Ab+ patients through 52 weeks in the RCP
- UPLIZNA offers a twice-yearly dosing schedule with 6 months of infusion-free time following the 2 initial doses 2 weeks apart when starting therapy
- And finally, UPLIZNA has an established gMG safety profile in a phase 3 trial with 238 patients, with the most common adverse reactions being headache and infusion-related reaction
Thank you for joining me to review the MINT study.